


Why Tennis Elbow and Shoulder Pain Keep Coming Back (And What Actually Works)
If your elbow or shoulder pain keeps resolving and then returning every time you pick the racket back up, the problem was likely never fully treated in the first place. That's not a reason to give up on tennis. It's a sign that the treatment needs to go deeper than rest and a few weeks of physical therapy. Dr. Ilana Etelzon, MD, double board-certified in Physical Medicine & Rehabilitation and Interventional Pain Management, sees this pattern constantly in tennis players, and she's found that once the actual cause is addressed, most patients get back to full play and stay there.
How Common This Actually Is
Tennis elbow has a reputation for being minor, but research puts lifetime prevalence among recreational tennis players at 40 to 50 percent. Shoulder pain is just as common. One often-cited figure found that about 24 percent of junior players report shoulder pain, climbing to roughly half of players in older age groups, and a recent systematic review puts shoulder tendinopathy at 25 to 48 percent of presentations in players over 18.
The two conditions also show up together more often than most players realize, and that's not a coincidence. Tennis strokes rely on a kinetic chain, the sequence that transfers force from the legs and core through the shoulder and into the arm and racket. When that chain breaks down anywhere, from fatigue, poor mechanics, or a weak core, the shoulder and elbow end up absorbing the extra load. A shoulder that's compensating for a breakdown elsewhere in the chain puts more strain on the elbow, and vice versa, which is part of why the two so often get treated as one problem instead of two separate ones.
What's Actually Happening in the Tendon
Despite the name, tennis elbow usually isn't inflamed in the way most people picture inflammation. Research on the tissue itself shows something closer to angiofibroblastic degeneration, meaning the collagen fibers break down and lose their normal structure. That distinction matters because it explains why rest alone, which is built to calm inflammation, often doesn't fix a tendon that has already started to degenerate.
Dr. Etelzon has seen this play out directly with patients. She describes a tennis player who had already been through physical therapy, with the pain settling down temporarily and then returning every time he went back to play. "PT was helping somewhat, but every time they went back to playing, the pain returned," she says. An ultrasound told the rest of the story. "We looked more closely at the tendon with ultrasound and identified changes consistent with chronic tendinopathy," Dr. Etelzon explains. "At that point, it wasn't necessarily about doing more PT. We needed to address the underlying tendon problem." That's where treatments like PRP come in, paired with a more targeted rehab program built around what the tendon actually needs.
Why Standard Treatment Often Doesn't Finish the Job
Conservative treatment resolves most cases of tennis elbow, but recurrence is a well-documented problem. One randomized trial found that corticosteroid injections delivered strong short-term relief and then reversed course, with 72 percent of patients experiencing a recurrence at one year, compared to 8 percent after structured physical therapy. The pattern Dr. Etelzon sees in her own patients lines up with that research, and it usually starts long before anyone walks into her office.
"One thing I've noticed is how many tennis players continue playing through pain for months before seeking treatment," Dr. Etelzon says. "By the time they come in, what may have started as a relatively minor issue has become a chronic problem." The location of the pain can also be misleading. "The pain isn't always coming from where they think it is," she explains. "Someone comes in complaining about their elbow, but you also have to look at their shoulder, wrist, and even their neck." Given how much the kinetic chain connects these joints, that pattern tracks with what the research on tennis shoulder and elbow injuries shows. Treating the elbow in isolation, without looking at what's happening up the chain, is part of why the pain comes back even after a course of PT that seemed to be working.

How to Actually Know Treatment Is Working
Pain scores alone can be misleading, since a tendon can feel quiet for a while and still be far from healed. Dr. Etelzon looks past what a patient reports in the moment and focuses on what they can actually do. "It's not just when a patient tells me their pain is better," she says. "It's important to know what they're actually able to do that they couldn't do before. Can they grip their racket without pain? Can they play longer? Are they recovering better after playing?"
She also tracks measurable markers during exam, including strength, range of motion, and tenderness at the site of the injury. The real test comes over time, not in a single visit. "When they're gradually getting back to playing without the same symptoms returning afterward, that's when I know we're making progress," Dr. Etelzon says. That standard, real function sustained over time, is what separates a tendon that's actually healed from one that's just temporarily calm.
Treating the Root Cause
Corticosteroid injections are still common for tennis elbow and shoulder pain because they work fast. The tradeoff shows up later. Multiple randomized trials comparing the two have found that corticosteroids outperform PRP in the first few weeks, then fall behind, with PRP patients continuing to improve over months while corticosteroid patients decline. A two-year follow-up of the same trial found PRP's advantage held steady well beyond the first year.
The difference comes down to what each treatment is actually doing. A corticosteroid injection calms the area down. PRP injections use concentrated platelets drawn from a patient's own blood to trigger the body's repair process directly inside the degenerated tissue, giving the tendon a real chance to rebuild instead of just quieting down for a while. For shoulder involvement tied to the same kinetic chain breakdown, the same regenerative approach often applies, paired with rehab that addresses the chain as a whole instead of treating the elbow and shoulder as two unrelated problems.
What Dr. Etelzon Wants Every Player to Know
After years of treating tennis players, Dr. Etelzon has a few things she repeats often enough that she considers them essential, even though they rarely make it into general articles about tennis injuries. The first is that tolerating pain is not the same as being safe from damage. "Just because you can play through the pain doesn't mean you should," she says. "A lot of athletes think that if they can tolerate the pain, they're not doing any additional damage."
The second is that calming pain down and actually healing the tendon are two different processes. "There's a difference between reducing inflammation and actually improving the health of a tendon," Dr. Etelzon explains. "Sometimes taking a short break and addressing the problem early can prevent months of frustration." And the goal, she's clear, was never just about getting through a match without pain. "My goal isn't just to get them pain-free. It's to get them back on the court and keep them there."
If tennis elbow or shoulder pain keeps resolving and then coming back every time you return to play, it's worth having the tendon actually evaluated instead of starting another round of rest and bracing. Schedule a consultation with Dr. Etelzon's team to find out what's really driving the pain and what it will take to put it behind you.


What Causes Knee Pain? Common Causes and When to Get Checked
What Causes Knee Pain?
Most knee pain comes down to one of three things: a torn meniscus, an injured ACL, or osteoarthritis. Figuring out which one you're dealing with is the fastest route back to stairs, long walks, and getting down on the floor with the grandkids without a second thought. Here is how to tell the causes apart, which signs mean it's time to get checked, and what you can do about it without surgery.
The Three Most Common Causes of Knee Pain
Alexandra DeFrance, PA-C, a board-certified physician assistant specializing in orthopedics and regenerative medicine at Pain Doctors Medical, sees the same three culprits again and again.
"The big three for me are meniscus tears, ACL tears, and osteoarthritis. The meniscus is the one that surprises people. You don't need to be sliding into second base. You squat down to grab a bag of potting soil, twist a little on the way up, and something catches. The ACL usually comes with a story. There's a pivot, sometimes a pop you can hear, and suddenly your knee feels like it belongs to somebody else."
Meniscus Tear
The meniscus is a C-shaped cushion of cartilage between your thigh bone and shin bone. Tears can happen in a single awkward twist or build slowly as the tissue ages. Common signs include pain along the inside or outside of the knee, swelling, and a catching or locking feeling.
ACL Tear
The anterior cruciate ligament keeps your shin bone from sliding forward and rotating too far. It tends to tear during quick pivots, sudden stops, or a bad landing. Swelling comes on fast, and the knee may feel loose or give way.
Osteoarthritis
Osteoarthritis is the gradual breakdown of the cartilage that lets the joint glide. It is the most common cause of long-term knee pain in adults over 40, and it usually causes morning stiffness or pain after sitting, plus pain that worsens with activity. It moves through four stages of osteoarthritis, from mild cartilage wear to bone-on-bone.
Knee Pain Without an Injury
If you can't point to a moment when it started, the answer is often arthritis.
"If you can't remember hurting it, my money's on arthritis. It creeps in. First, it's the stairs. Then it's getting out of a low car. Then one day you realize you've been picking restaurants based on how close you can park."
Overuse can also play a role. Tendons around the kneecap, the bursa sacs that cushion the joint, and the band of tissue along the outer thigh can all get irritated by repetitive activity, extra body weight, or changes in how you walk.

How to Tell If Your Knee Pain Is Serious
Pain that fades after a day of rest is usually your knee asking for a break. Pain that shapes your plans deserves a closer look.
"My rule is simple. If your knee is making decisions for you, come in. You're skipping the walk, saying no to the trip, planning your whole day around it. And sharp, shooting pain gets my attention faster than a dull ache. A dull ache usually means irritation. Sharp can mean something is torn or pinched, and that's worth a look."
Other signs to take seriously include a knee that locks, gives way, or swells quickly, and any pain that wakes you at night.
Treatment Options for Knee Pain Besides Surgery
Surgery is one option on a long list, and for many people, it sits near the bottom.
"People come in thinking it's surgery or nothing. It's a long list. There's regenerative medicine, so PRP and stem cells. There are cortisone and gel injections, which can buy you some time. And there's shockwave and laser, which most people have never heard of and then can't stop telling their friends about."
At Pain Doctors Medical, care follows a four-part approach: Reveal, Repair, Restore, Renew. It starts by finding the true source of the pain, then builds a plan around four core regenerative medicine therapies:
- PRP injections place concentrated growth factors from your own blood into the damaged joint, tendon, or ligament under ultrasound guidance.
- Bone marrow concentrate injections use your own cells, processed under the Regenexx protocol, for more advanced joint damage.
- MLS laser therapy calms inflammation and improves circulation around the knee.
- Shockwave therapy, also called ESWT, sends acoustic pressure waves into sore tissue to increase blood flow and support repair.
Back to Walking Without Thinking About It
Some patients want results without a single needle. DeFrance had one who said exactly that.
"She had pain on the inside of her knee, and she was very clear with me: no injections, no surgery. Fair enough. So we did shockwave, which feels like a deep, dull thump right on the sore spot, and laser, which you barely feel at all. It's almost boring. A few weeks in, she was walking without thinking about her knee. That's the whole goal. You stop noticing it."
Every knee is different, and results vary. An evaluation is the only way to know which approach fits you.
Get Your Knee Evaluated
Knowing what causes your knee pain is the first step toward fixing it. Pain Doctors Medical treats knee pain at offices in Brooklyn, Newark, Perth Amboy, and Clifton, led by Dr. Ilana Etelzon, MD, a double board-certified physician in Physical Medicine and Rehabilitation and Interventional Pain Management. Take the Pain Quiz or schedule a consultation to find out what's behind your knee pain and how to get back to the things you love.

What Are the 4 Stages of Osteoarthritis? A Stage-by-Stage Guide
Osteoarthritis moves through four stages, from faint cartilage wear you may never feel to bone rubbing on bone. Knowing your stage tells you which options are still open, and for most people, that list is longer than they were told. Here is what each stage looks like, what it feels like, and how the team at Pain Doctors Medical helps patients get back to the walks, gardens, and pickleball courts they miss.
What Osteoarthritis Is and What Causes It
Osteoarthritis is the gradual breakdown of the cartilage that cushions the ends of your bones. Most people picture simple wear and tear. Alexandra DeFrance, PA-C, a board-certified physician assistant specializing in orthopedics and regenerative medicine at Pain Doctors Medical, sees something more active going on.
"Everyone pictures arthritis like the tread wearing off an old tire. That's part of it. What I actually see in the exam room is inflammation. The joint gets irritated, it calls in the inflammatory cells to clean things up, and then those cells overstay their welcome and start chewing on the cartilage. Age sets the stage. An old ski injury can set the stage. And sometimes you can thank your mother for your knees."
Those three drivers, age, past injury, and genetics, explain why two people with the same birthday can have very different joints. A torn meniscus at 30 can show up as arthritis at 50. A family history can speed the timeline along.
The 4 Stages, From Minor to Bone on Bone
Clinicians grade osteoarthritis on a scale of one to four, usually by reading an X-ray alongside your symptoms.
"We grade it one through four. A one is barely anything, maybe a little narrowing on the X-ray that you'd never feel. A four is bone on bone. Patients will say 'my doctor told me I'm bone on bone' like it's a verdict. It's a description. It tells me where we're starting."
Stage 1: Minor
Cartilage shows the first small signs of wear, and tiny bone spurs may start to form. Most people feel nothing, or a little stiffness after a long day on their feet. This stage usually turns up by accident on an X-ray taken for something else.
Stage 2: Mild
Bone spurs become visible on imaging, though the space between the bones still looks close to normal. The joint starts to talk back: stiffness after sitting through a movie, an ache after a long walk, a knee that needs a minute to warm up in the morning.
Stage 3: Moderate
The cartilage thins noticeably, and the joint space narrows. Inflammation becomes a regular visitor, so swelling, pain with stairs or kneeling, and a creaky, grinding feeling are common. This is often when people start quietly editing their lives, skipping the hike or choosing the restaurant with the closest parking.
Stage 4: Severe
Most of the cartilage is gone, and bone meets bone. Pain can show up at rest and at night, and imaging sometimes reveals bone marrow edema, a kind of bruise inside the bone. This is the stage where a joint replacement usually enters the conversation.
The Best Treatment for Osteoarthritis Starts With Calming the Joint
If inflammation drives the damage, quieting it is the first job. DeFrance puts regenerative medicine at the top of her list.
"My goal is to calm the joint down. That's what regenerative medicine does well. We take your own platelets, or your own cells, and put them exactly where the damage is, so the joint starts getting signals to repair instead of signals to keep fighting. Keep the inflammatory cells out of the room and the whole joint behaves differently."
At Pain Doctors Medical, treatment follows a four-part approach: Reveal, Repair, Restore, Renew. The first visit focuses on finding the true pain driver. From there, care is built around four core therapies:
- PRP injections concentrate growth factors from your own blood and place them into the joint, tendon, or ligament under image guidance. PRP often fits well in stages one through three.
- Bone marrow concentrate injections use your own cells, processed under the Regenexx protocol, and are typically considered for more advanced joints.
- MLS laser therapy calms inflammation and improves circulation around the joint, creating a better environment for repair.
- Shockwave therapy sends acoustic pressure waves into sore tissue to boost blood flow and support recovery in the tendons and ligaments around the joint.
Every injection is performed under ultrasound guidance, so the treatment lands where the problem lives.
From Bone on Bone Back to Pickleball
Stage four sounds final. One of DeFrance's patients would disagree.
"She came in with a date on the calendar for a knee replacement. Bone on bone, and the X-ray was not subtle about it. She wanted one more opinion before she handed her knee over. We did stem cells and PRP into the joint, into the ligaments around it, so the knee would feel stable again, and into the bone itself, because her MRI showed bone marrow edema. That's basically a deep bruise inside the bone, and it throbs. She got real relief. She canceled the surgery. Last I heard, she was back playing pickleball, and from what I'm told, talking a little trash on the court."
Results vary from person to person, and not every stage four joint is a candidate. A thorough evaluation is how you find out which group you're in.
Find Out Your Stage
The earlier you know your stage, the more options you keep. Pain Doctors Medical treats osteoarthritis at offices in Brooklyn, Newark, Perth Amboy, and Clifton, led by Dr. Ilana Etelzon, MD, a double board-certified physician in Physical Medicine and Rehabilitation and Interventional Pain Management. Take the Pain Quiz or book a consultation to learn where your joint stands and what it will take to get you moving again.

Radial Shockwave Therapy: A Non-Surgical Path Back to the Activities You Love
Chronic tendon and muscle pain can limit the activities that used to come easily, at work, during a workout, or just moving through an ordinary day. Radial shockwave therapy offers a way to help bring you back to the person you were before pain. Pain Doctors Medical, led by Dr. Ilana Etelzon, a physician double-board certified in Physical Medicine and Rehabilitation and Interventional Pain Management, uses this acoustic wave technology to help patients regain strength and mobility before surgery ever becomes part of the conversation.
With offices in Brooklyn, New York, and Clifton, Newark, and Perth Amboy, New Jersey, Pain Doctors Medical treats patients across the region seeking a non-surgical path back to movement.
How It Works
Radial shockwave therapy delivers acoustic pressure waves through a hand-held applicator pressed against the skin. A projectile inside the device accelerates toward the tip, and the resulting pressure wave spreads outward through the tissue, with its energy concentrated near the point of contact. Physiatrist Joshua Romero, M.D. of Mayo Clinic, explains that this mechanical stimulus triggers cellular changes that prompt cell migration, new blood vessel growth, and shifts along pain pathways. In plain terms, the treatment nudges the body's own repair systems into gear.
This is different from a general massage or a topical treatment. Radial shockwave therapy reaches deeper structures where scar tissue, calcification, and chronically tight trigger points tend to live, and it does so without needles or incisions.
Common Conditions Treated
Radial shockwave therapy is best suited for tendon and soft tissue conditions, including:
- Tendinopathy of the elbow, shoulder, knee, or Achilles
- Plantar fasciitis
- Calcific deposits in tendons
- Bursitis
- Myofascial pain syndrome and muscle trigger points
- Scar tissue restricting mobility after an injury
A randomized controlled trial published in the Journal of Clinical Medicine found that patients with acute low back pain who received radial shockwave therapy alongside physical therapy reported meaningful pain improvement compared with those who received a placebo. That kind of evidence is part of why the therapy has become a standard tool for physiatrists treating musculoskeletal pain.
What to Expect During Treatment
A typical radial shockwave session at Pain Doctors Medical takes about 10 to 20 minutes. Dr. Etelzon or her clinical team applies a coupling gel to the treatment area, then guides the applicator over the site of pain. Because pain is sometimes felt away from its actual source, patient feedback during the session helps pinpoint the exact area that needs treatment. Most protocols call for two sessions per week over three to four weeks, though the exact plan depends on the condition being treated.

Does Radial Shockwave Therapy Work?
Alexandra DeFrance, PA-C, a physician assistant at Pain Doctors Medical, specializing in orthopedics and regenerative medicine, has seen the therapy change the course of recovery for patients who had tried everything else. She points to a 47-year-old patient who came in after a motor vehicle accident with persistent neck and lower back pain, along with muscle spasms so severe she struggled to look over her shoulder, drive, or sleep. The patient had already completed a full course of supervised physical therapy and chiropractic care two to three times a week without lasting relief.
“Radial shockwave therapy was highly successful for her because it specifically targeted her chronic myofascial pain syndrome and active trigger points,” DeFrance said.
Her case reflects a pattern that DeFrance and Dr. Etelzon often see. Patients who have exhausted conservative care still have options that do not involve surgery.
How Long Does It Take for Radial Shockwave Therapy to Work?
Many patients notice some reduction in pain shortly after their first session, largely because the acoustic waves interrupt local pain signaling. More durable improvements in pain and function typically build over 8 to 12 weeks as tissue remodeling continues, according to Mayo Clinic's Dr. Romero. Patience through the full course of sessions matters more than the first appointment.
How Long Do Shockwave Treatments Last?
Results depend on the condition being treated and how consistently the recommended protocol is followed. Most patients complete a series of sessions over three to four weeks, and the tissue changes triggered during that window continue to develop for weeks afterward. For chronic tendon conditions, many patients maintain their improvement well beyond the treatment period, particularly when shockwave therapy is paired with a supportive physical therapy or strengthening program.
How Painful Is Shockwave Therapy?
Most patients describe the sensation as a deep, dull ache rather than sharp pain, and it is generally well tolerated without anesthesia. Some discomfort at the treatment site is expected. It confirms the waves are reaching the correct tissue. Intensity can be adjusted during the session based on patient feedback, and most people return to light daily activity the same day.
What Are the Negative Side Effects of Shockwave Therapy?
Radial shockwave therapy carries a favorable safety profile. Documented side effects include mild skin redness, bruising, swelling, or tingling at the treatment site for up to 24 hours. Less commonly, patients can experience localized hematoma, nerve irritation, or temporary soreness. The treatment is not recommended for patients who are pregnant or who have a malignant tumor, severe coagulopathy, or certain bone or nerve conditions in the treatment area, which is why a full evaluation with Dr. Etelzon precedes any treatment plan.

What Not to Do After Shockwave Therapy?
Patients are generally advised to avoid intense exercise, heavy lifting, or activities that stress the treated area for a day or two after each session. Nonsteroidal anti-inflammatory medications are typically discouraged in the days surrounding treatment, since inflammation is part of how the therapy stimulates tissue repair. Ice should only be used if a provider recommends it, as it can counteract the healing response the treatment is designed to trigger. Following the specific aftercare plan from Dr. Etelzon's team gives the tissue the best chance to remodel properly between sessions.
How Much Does Radial Shockwave Therapy Cost?
Cost varies based on the number of sessions recommended and the condition being treated. Radial shockwave therapy is not covered by most insurance plans for many conditions, so Pain Doctors Medical works directly with patients to develop a treatment plan and offers flexible payment options. The best way to get an accurate estimate is a consultation, where Dr. Etelzon can evaluate the condition and outline exactly what a course of treatment would involve.
For patients who have tried physical therapy, medication, and rest without lasting relief, radial shockwave therapy offers a next step that does not require surgery or a long recovery. Scheduling a consultation with Dr. Etelzon is the first step toward finding the right treatment plan.
BMAC Procedure (Bone Marrow Aspirate Concentrate): What to Expect
A BMAC procedure, short for bone marrow aspirate concentrate, uses concentrated cells drawn from your own bone marrow to support the repair of joints, tendons, and other soft tissue. It is an outpatient treatment, completed in a single office visit, using your body's own biology rather than donor tissue or synthetic material. This guide covers what actually happens during a BMAC procedure, how it compares to other options, and what recovery looks like.
What Actually Happens on Treatment Day
Alexandra DeFrance, PA-C, a physician assistant specializing in orthopedics and regenerative medicine at Pain Doctors Medical, walks every new patient through the BMAC procedure before it begins.
"We numb the back of the hip well, and I draw marrow from the pelvis through a small needle," DeFrance explains. "Most people describe deep pressure for a few seconds rather than sharp pain." The sample is processed and concentrated down to the specific cells needed for repair, and DeFrance then places it directly into the injured tissue using ultrasound or fluoroscopic guidance. According to Cleveland Clinic, the full BMAC procedure, from bone marrow aspiration through the final injection, typically takes about two hours from start to finish. Patients walk out the same day, and most report soreness at the hip site for a day or two afterward.
BMAC or PRP: How the Decision Gets Made
Pain Doctors Medical offers both PRP and a BMAC procedure, and DeFrance evaluates each patient individually rather than defaulting to one option. Her explanation is straightforward. PRP sends signals to the body's existing repair cells. Bone marrow concentrate sends signals and the cells themselves.
If the tissue still has enough of its own repair capacity, a mild tendon issue or early cartilage wear, platelets alone are often enough to get the job done. DeFrance turns to a BMAC procedure when there is genuine structural loss involved: thin cartilage, a larger tear, a ligament that has been loose for years, or a patient who already tried platelets elsewhere and only got partway to relief. Age plays a role, too. The less a patient's own repair response does on its own, the more DeFrance wants to bring actual cells to the site rather than relying on signals alone.
Other Options You May Have Considered
Most patients who look into a BMAC procedure have already tried something else first. Physical therapy, cortisone injections, anti-inflammatory medication, or simply resting the joint are all reasonable first steps, and many people get real relief from them. Some patients have also looked into surgery, including a joint replacement, a rotator cuff repair, or a cartilage procedure, and want to understand what else exists before committing to that path.
Why a BMAC Procedure Might Be Right for You
A BMAC procedure tends to fit patients who have more structural loss than platelet therapy alone can address: thin cartilage, a larger tear, a ligament that has been loose for years, or a joint that has not fully responded to physical therapy or a PRP injection. For many patients, it becomes the next step that uses their own biology before turning to something more invasive.
Why the Details of Processing and Placement Matter
BMAC procedures are widely advertised, but DeFrance points out that the results patients experience often come down to two specific details: how the cells are concentrated and exactly where they are placed.
At Pain Doctors Medical, cells are processed under the Regenexx protocol, a standardized approach that concentrates and checks the sample rather than relying on whatever a countertop kit happens to produce. Every injection is then guided by imaging. If a tear is only a few millimeters wide, an injection into the general area of the joint is not the same as an injection into the tear itself. Regenexx also tracks outcomes across its network of providers, which means DeFrance can speak to real outcome data for patients with a similar problem rather than relying on general marketing claims.
Recovery After a BMAC Procedure
The recovery timeline for a BMAC procedure tends to be more forgiving than people expect. Patients walk out the same day the procedure is done. DeFrance typically asks for about two weeks of easing off the treated joint before gradually reintroducing load on purpose.
Most patients return to normal daily activity within a week or two, with a return to real exercise or training around six to eight weeks. The part patients most often underestimate is the tissue timeline underneath the surface. Cells take months to fully remodel the area, so while many notice a change around six to eight weeks, the larger gains tend to show up between three and six months out.
A Plan Built Around Your Own Biology
A BMAC procedure works with the body's own healing process, giving it more to work with rather than bypassing it. Pain Doctors Medical, led by Dr. Ilana Etelzon, MD, and Alexandra DeFrance, PA-C, has particular experience helping active women in midlife get back to the activities they love, though the same regenerative medicine approach applies to anyone dealing with a joint or tendon injury that has not fully resolved. With locations in Brooklyn, Clifton, Newark, and Perth Amboy, Pain Doctors Medical builds each plan around the specific joint, the specific tear, and the specific patient.
Frequently Asked Questions
Can BMAC regrow cartilage?
BMAC works by creating a better healing environment for the joint rather than regenerating large areas of missing cartilage outright. It calms inflammation and supports the tissue that remains. Patients with mild to moderate cartilage wear tend to see the most benefit, while more severe, bone-on-bone arthritis may need to be paired with other treatments or evaluated for different options.
How painful is BMAC?
Most patients describe a BMAC procedure as uncomfortable rather than painful. The area over the hip is numbed before the bone marrow is drawn, so patients typically feel deep pressure for a few seconds rather than sharp pain. Some soreness at the hip and injection sites is common for a day or two afterward, similar to a deep muscle ache.
How long after a BMAC injection do you feel the effects?
Every patient's timeline is a little different, but many notice an initial change around six to eight weeks after treatment. The bigger improvements tend to show up between three and six months, since the cells need that time to fully remodel the injured tissue.
Will they put you to sleep for a bone marrow biopsy?
For an outpatient BMAC procedure like the ones performed at Pain Doctors Medical, patients stay awake. The treatment area is numbed with a local anesthetic, so there is no need for general anesthesia or sedation. Some hospital-based procedures that combine bone marrow aspiration with surgery may use sedation, but that is a different setting than an in-office regenerative treatment.

The Body's Natural Healing Mechanisms and Why That Changes at Midlife
If you have noticed your body does not bounce back the way it used to, you are far from alone. A recent thread on Reddit's r/Aging, called "Body Falling Apart From 50", gathered dozens of people describing that same feeling: aches that linger, injuries that used to heal in weeks now taking months, or old injuries that never quite go away.
That feeling is real, and it is not the whole story. The body's natural healing mechanisms are still there, at any age. They do not disappear at 50, 60, or 70. What often changes is how easily your body can access them on its own, and that is where the right doctor makes the difference.
If you have been told your only options are surgery, months of physical therapy, or opioids for pain management, it is normal to feel frustrated, even hopeless. Those paths can feel disconnected from what your body actually needs, especially when deep down it feels like healing should happen more naturally than that. The capacity to heal is already inside you. It always has been. What you may need is help accessing it.
The Body's Repair Crew
When a joint or tendon is damaged, the body responds almost instantly. Blood, platelets, and repair cells flood the area, and those cells get to work laying down new collagen. Within a few weeks, most injuries in a younger body are simply resolved, often without the person giving it much thought.
Alexandra DeFrance, PA-C, a board-certified physician assistant specializing in orthopedics and regenerative medicine at Pain Doctors Medical, describes these natural healing mechanisms as a supply and demand system.
"When you sprain an ankle or strain a tendon, your body floods the area with blood, platelets, and repair cells," DeFrance says. "Those cells lay down new collagen, and over a few weeks, you are back. What changes after 50, and especially through menopause, is the supply. There are fewer repair cells, they respond more slowly, and the drop in estrogen makes tendon and ligament tissue less resilient. The instructions are still there. The workforce just got smaller."
Why an Injury Sometimes Refuses to Heal
Most people assume an injury that will not heal is simply a bigger injury. Often, it is something else entirely. DeFrance points to three patterns she sees most often in patients across Brooklyn, Clifton, Newark, and Perth Amboy whose natural healing mechanisms seem to have stalled on an old strain or sprain.
"Usually one of three things," DeFrance explains. "The joint keeps getting loaded the wrong way because nobody corrected the mechanics, so the tissue never gets a quiet stretch to heal. Or the blood supply in that spot is poor, which is true for a lot of meniscus and rotator cuff tears. Or the damage is simply bigger than what the body can bridge on its own. I also see people who rested for six months and lost the muscle that was protecting the joint, so now it is under more load, not less."
As frustrating, or even hopeless, as this can feel, especially the older you get, there are real solutions. An injury that has stalled for months or years is not proof that your body has stopped healing. More often, it is a sign that something specific is blocking the process, and that something can usually be identified and addressed. This is where finding the right doctor changes everything. A physician who takes the time to understand your natural healing mechanisms, rather than treating only the symptom in front of them, can get to the actual root of the problem and help your body do what it already knows how to do.
How Regenerative Medicine Supports Your Body's Own Process
At Pain Doctors Medical, treatment starts with the whole picture, including everything connected to the joint that hurts. "An injection is a product. What we do is a plan," DeFrance says. "I look at the whole chain, because a knee is very often paying for a hip." That plan follows the Regenexx protocol at every Pain Doctors Medical location, so the concentration returning to a patient's body is processed to a known, tracked standard rather than whatever a bedside kit happens to produce. Every PRP or bone marrow placement is guided by ultrasound or fluoroscopic imaging, so the cells land directly in the injury rather than somewhere nearby. DeFrance also follows her patients well after the appointment itself. As she puts it, "Healing is a process, not an appointment."
A Rotator Cuff That Healed On Its Own Terms
One story has stayed with DeFrance, maybe because so many patients see themselves in it. A woman in her early 60s came in already resigned to surgery. She had lived with shoulder pain for two years, quietly leaning on her neck and shoulder blade to do the work her rotator cuff used to handle, and a surgery date was already on the calendar. If any of that sounds familiar, the slow compensating, the appointments that come and go without real answers, you are not alone in that either.
"The tear on imaging was real but small," DeFrance recalls. "What was keeping it open was how much she was compensating through her neck and shoulder blades." Rather than send her straight into surgery, DeFrance treated the tear with the patient's own bone marrow cells and corrected the mechanics feeding the problem. Months later, repeat imaging showed the tear had filled in. "Her body did that," DeFrance says. "We just gave it a fair shot."
For a patient who had spent two years bracing for an operation, that outcome was deeply personal. It was the difference between believing her body had failed her and realizing it had been trying to heal the whole time.
What This Means for You
Healing does not stop at any age. The body's natural healing mechanisms are still working, even when an injury feels stuck. For people across Brooklyn, Clifton, Newark, and Perth Amboy who feel like their body has stopped cooperating, the right doctor can help you find and access those mechanisms again, rather than simply managing the pain around them.
Pain Doctors Medical, led by double board-certified physician Dr. Ilana Etelzon, MD, along with Alexandra DeFrance, PA-C, specializes in identifying exactly where healing has stalled and why, then building a regenerative medicine plan around restoring your body's own natural healing mechanisms rather than masking the symptom on top of it.

How Long Does Tendonitis Last? Recovery Timeline Explained
Most tendonitis settles down within two to six weeks. Rest, ice, a temporary change in activity, and the tendon quiets back down. That is the version most people expect, and for a first flare-up it is usually what happens.
When pain is still there at three months, that is useful information. It means something specific is preventing the tendon from finishing its repair, and that something can be identified and treated. The waiting is what tends to be unproductive, so the more helpful question is not how much longer to wait. It is what is actually happening inside the tendon.
The typical tendonitis timeline
Tendon pain generally falls into three windows.
Two to six weeks. True acute tendonitis, meaning genuine inflammation from a recent overload, tends to resolve in this range with relative rest and activity modification. Pain is sharp with use and settles with rest.
Six weeks to three months. Pain that improves and then returns every time activity picks back up. The tendon is repairing, and the repair is not keeping pace with the demand being placed on it.
Beyond three months. At this stage the tissue has usually changed. Inflammation is no longer the main driver, which is why anti-inflammatory approaches stop producing results.
Why tendon pain lingers past the three month mark
Once tendon pain persists, the underlying problem is typically degeneration rather than inflammation. Clinically this is called tendinosis. The collagen fibers that give a tendon its strength become disorganized, the tissue thickens and loses its normal structure, and tiny partial tears can develop. Tendons also carry a limited blood supply compared with muscle, so repair is slow by design.
This distinction matters for treatment. Rest calms an inflamed tendon. Rest does very little for a degenerated one, because the tissue is not irritated. It is structurally weakened. That is the reason so many patients describe months of good behavior followed by pain returning the moment they go back to hiking, gardening, or lifting anything meaningful.
Finding the reason healing stalled
A lingering tendon needs an explanation, and that explanation is usually specific to the patient.
"When tendon pain lasts for months instead of weeks, I look beyond inflammation to determine why the tendon isn't healing," Dr. Etelzon explains. "I evaluate the patient's movement patterns, biomechanics, muscle imbalances, activity level, and overall health, and use diagnostic ultrasound or MRI to identify tendon degeneration or partial tears. The goal is to find and treat the underlying cause, not just relieve the pain."
Diagnostic ultrasound is particularly useful here because it shows the tendon in motion. Thickening, disorganized fibers, partial tearing, and calcification are all visible, and the tendon can be assessed while the joint moves through its range. Two people with the same diagnosis on paper often have very different tendons on the screen, and their treatment plans should reflect that.
Contributing factors that commonly show up during evaluation include mechanical loading patterns that keep re-irritating the same fibers, weakness in the muscles surrounding the joint, hormonal changes that affect collagen quality, thyroid or metabolic conditions, and certain medications. Addressing the tendon alone, while leaving the cause in place, tends to produce a temporary result.
A different approach to chronic tendon pain

Standard advice for tendonitis has a ceiling. Once a tendon has degenerated, more rest does not restore its structure.
"At Pain Doctors Medical, we don't believe in simply telling patients to rest and wait when tendon pain has become chronic," says Dr. Etelzon. "We identify the underlying cause using a comprehensive evaluation and advanced ultrasound imaging, then create a personalized treatment plan. Depending on the condition, this may include targeted rehabilitation, shockwave therapy, and image-guided regenerative treatments such as PRP or bone marrow concentrate to support the body's natural healing process. Our goal is to restore function, reduce pain, and help patients get back to the activities they love, not just temporarily mask symptoms."
Several options are used depending on what the imaging shows.
Shockwave therapy delivers acoustic energy into the tendon to stimulate blood flow and prompt the repair response in tissue that has gone dormant. It works well for tendons that are degenerated without significant tearing.
PRP injections concentrate the growth factors from a patient's own blood and place them directly into the damaged tissue under ultrasound guidance. Those growth factors signal the body to rebuild collagen where the tendon has broken down.
Bone marrow concentrate, also called stem cell injections, is drawn from the patient's own bone marrow and used when degeneration is more advanced or a partial tear is present. It brings a broader set of cells and signaling factors to the repair.
Percutaneous tenotomy removes the degenerated tissue itself through a very small opening, again under ultrasound guidance, which allows healthier tissue to take over. This is often the right choice when a tendon has thick scarred or calcified tissue that will not respond to stimulation.
The common thread is that each of these works on the tendon's structure rather than masking the signal coming from it.
What recovery actually looks like
Timelines are the part patients most want pinned down, and they are reasonable to ask about.
"Every patient heals at a different pace, but most begin noticing gradual improvement within 4 to 8 weeks, with more significant gains over 3 to 6 months as the tendon continues to remodel and strengthen," Dr. Etelzon says.
That pattern reflects how tendons repair. Collagen is laid down first, then organized and strengthened over months as controlled load is reintroduced. Improvement arrives in steps rather than a single moment, and the later gains are often the ones that make the difference for activity.
Rehabilitation runs alongside the procedure rather than after it. Progressive loading tells the new collagen how to organize, and activity is modified during the window when the tendon is rebuilding so the same overload pattern does not restart the cycle.
Returning to the activities that matter
For an active woman in her fifties or sixties, the goal is rarely just less pain. It is confidence on a trail, a full afternoon in the garden, or an hour of tennis without paying for it the next day.
"Our goal isn't just to reduce pain," Dr. Etelzon says. "It's to restore the tendon so patients can confidently return to activities like hiking, gardening, or exercising while minimizing the risk of reinjury."
That last part is what separates a treated tendon from a rested one. A tendon that has been rebuilt and progressively reloaded can handle demand. A tendon that has simply been left alone for six months has lost strength and tends to fail again at the first real test.
Does this sound like you?
If tendon pain has outlasted the timeline you were given, it is worth finding out why. Pain Doctors Medical offers diagnostic ultrasound evaluation and image-guided regenerative treatment at locations in Brooklyn, Clifton, Newark, and Perth Amboy.
Request a consultation to have your tendon evaluated and get a clear answer about what recovery looks like for you.

Stem Cell Therapy for Back Pain: How Bone Marrow Concentrate Injections Actually Work
A Patient's Path Back to an Active Life
Dr. Ilana Etelzon of Pain Doctors Medical shares a case that reflects what she sees often in her practice: a patient who had tried nearly everything before finding her way to regenerative medicine.
A 55-year-old woman presented to our office with chronic lower back pain radiating into both legs. She had been struggling with persistent symptoms for several years despite extensive conservative treatment, including physical therapy, physician-directed home exercises, activity modification, anti-inflammatory medications, and multiple epidural steroid injections. Although the injections provided only temporary relief, her pain consistently returned, limiting her quality of life.
The patient reported significant difficulty performing everyday activities such as cooking, grocery shopping, hiking, traveling, and caring for her family. She wished to avoid additional steroid injections and was reluctant to undergo spine surgery.
After a comprehensive evaluation, including a detailed physical examination and review of her imaging studies, she was determined to be an appropriate candidate for a minimally invasive regenerative treatment designed to address the underlying source of her pain rather than simply mask the symptoms.
Over the weeks following treatment, she experienced progressive improvement in both her lower back pain and the pain radiating into her legs. As her recovery continued, she was able to return to the activities she enjoyed most, including cooking, hiking, traveling, and caring for her family without significant limitations. She no longer required pain medications, additional physical therapy, or further steroid injections.
Most importantly, she was able to avoid spine surgery while regaining an active lifestyle and a substantially improved quality of life. She expressed tremendous satisfaction with her outcome and was grateful to return to living life on her own terms.
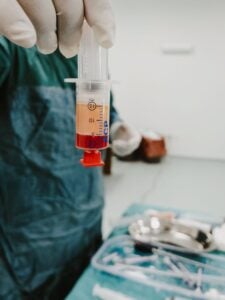
The treatment behind this recovery is a bone marrow concentrate injection, often called BMAC. The procedure draws a small sample of the patient's own bone marrow, concentrates the cells and growth factors within it, and delivers that concentrate directly to the site of injury using image guidance. For patients who want to avoid spine surgery and long term reliance on steroid injections, it offers an option that targets the source of the pain instead of covering it up.
The Pain Doctors Medical Approach to BMAC
Dr. Etelzon is a Regenexx Certified Core Provider, a distinction that shapes how her practice performs bone marrow concentrate injections from start to finish.
One of the biggest differences in our approach is that we don't simply perform a bone marrow concentrate (BMAC) injection. We follow a comprehensive, evidence-informed protocol designed to maximize precision and optimize the biologic environment for healing.
As a Regenexx Core Provider, I have undergone extensive advanced training in image-guided orthobiologic procedures and follow standardized protocols developed through years of clinical experience and ongoing research. Every patient undergoes a thorough evaluation to determine whether regenerative treatment is appropriate and to identify the specific structures responsible for their pain. Careful patient selection is one of the most important factors in achieving successful outcomes.
Our procedures are performed using high-resolution ultrasound and fluoroscopic guidance to ensure accurate placement of the biologic into the intended target tissues. Rather than treating only a single painful area, we frequently evaluate and address all of the structures contributing to dysfunction, including joints, ligaments, tendons, muscles, and, when appropriate, the spine, creating a comprehensive treatment plan tailored to the individual patient.
Another key difference is our attention to biologic preparation and rehabilitation. Bone marrow concentrate is processed according to established protocols, and treatment is often complemented by platelet-rich plasma (PRP), platelet lysate, or platelet-poor plasma (PPP) when clinically indicated. Patients also receive individualized rehabilitation guidance, activity modification, and follow-up to support recovery and optimize long-term function.
Being a Regenexx Core Provider does not guarantee a particular outcome, and no regenerative treatment is effective for every patient. However, it does mean that patients are treated using standardized protocols, advanced image-guided techniques, rigorous training standards, and an evidence-informed approach that emphasizes precision, safety, and appropriate patient selection. These principles are designed to give patients the best opportunity for a successful outcome while helping many avoid or delay more invasive procedures when clinically appropriate.
When Surgery Is Still the Right Path
Regenerative treatment is not the answer for every patient, and Dr. Etelzon is candid about where its limits are and how she determines the right course for each person she sees.
One of the most important conversations I have with every patient is understanding that regenerative medicine is incredibly powerful, but it is not the right solution for everyone. My responsibility is not simply to perform a procedure: it's to determine whether that procedure gives the patient a realistic chance of avoiding surgery.
There are situations where regenerative treatment alone is unlikely to provide the desired outcome. Patients with progressive neurologic weakness, significant spinal instability, severe deformity, advanced joint destruction, certain complete tendon ruptures, infections, fractures requiring stabilization, or conditions such as cauda equina syndrome often require prompt surgical evaluation. In these cases, delaying surgery could actually worsen the outcome.
The key is determining why the patient has pain. I spend considerable time reviewing imaging, performing a comprehensive physical examination, and correlating the two. I want to identify the true pain generators, not just the abnormalities seen on an MRI. Many patients are told they need surgery based solely on imaging, yet their symptoms may actually arise from treatable ligaments, tendons, joints, muscles, or other structures that have never been properly evaluated.
When appropriate, we take a comprehensive, precision-based approach. Rather than focusing on a single painful spot, we evaluate the entire functional unit and address all of the structures contributing to the patient's symptoms. That may include treating joints, supporting ligaments, tendons, muscles, and other stabilizing tissues using advanced image-guided regenerative techniques, combined with individualized rehabilitation, activity modification, and ongoing follow-up. The goal is not simply pain relief, it is restoring function and improving the body's ability to heal.
Only after I am confident that we have appropriately evaluated the patient and determined whether a regenerative approach is likely to help do we discuss treatment. If I believe surgery offers the best chance for recovery, I will tell my patient that honestly and refer them to an appropriate surgeon. My priority has always been doing what is best for the patient, even when that means recommending against a procedure in my own office.
For many carefully selected patients, regenerative medicine can help reduce pain, improve function, and potentially delay or avoid surgery. However, the best outcomes come from proper diagnosis, meticulous patient selection, precise image-guided treatment, and knowing when regenerative medicine has reached its limits. That commitment to individualized care is what allows us to confidently pursue every reasonable option before recommending surgery while never compromising patient safety.
Finding Out If You're a Candidate
Pain Doctors Medical evaluates candidates for bone marrow concentrate injections and other regenerative treatments at its Brooklyn, Clifton, Newark, and Perth Amboy locations. A consultation with Dr. Etelzon includes a review of imaging, a physical examination, and an honest conversation about whether regenerative medicine is the right next step, or whether a surgical referral makes more sense.
Schedule a consultation to find out which path fits your situation.

Regenerative Medicine for Shoulder Pain: Can You Actually Avoid Surgery?
Shoulder pain has a habit of quietly editing a life. The overhead reach for a coffee mug, the swing on the back nine, lifting a grandchild off the ground, these movements start to feel like negotiations instead of small, automatic moments. For many women in their fifties, sixties, and seventies, regenerative medicine is changing what comes next, offering a path back to those movements that do not start with a surgical consult.
Regenerative medicine for shoulder pain uses concentrated platelets or bone marrow-derived cells, drawn from the patient's own body, to target the specific tendon, ligament, or joint tissue causing the problem. For rotator cuff tendinopathy, partial tears, and early arthritic changes, this approach gives the tissue the biologic material it needs to repair itself, rather than removing or replacing what is already there. That is the appeal driving so many patients to research this option before they ever book a surgical consultation.
At Pain Doctors Medical, this approach is led by Dr. Ilana Etelzon, MD, a double board-certified interventional pain and physical medicine and rehabilitation physician and a certified Regenexx Core Provider. Shoulder pain is one of the most common reasons patients come to her for regenerative medicine, and her process for getting there starts with a real diagnosis, not a sales pitch.
A Diagnosis Comes Before Any Treatment Decision
"Every shoulder pain patient undergoes a detailed evaluation, including a physical exam, diagnostic ultrasound, and imaging review when needed," Dr. Etelzon explains. "The goal is to identify the exact source of pain before considering treatment."
Ideal candidates are patients with tendon, ligament, labral, or arthritic conditions that have not responded to conservative care. Complete tears requiring surgery, active infection, and severe joint destruction typically rule a patient out for regenerative treatment, which is part of why the evaluation matters as much as the procedure itself.
PRP or PRP With Bone Marrow Concentrate: The Decision Behind the Decision
"PRP alone is often an excellent option for milder rotator cuff tendinopathy and small partial tears," says Dr. Etelzon. For more significant tissue degeneration, larger partial tears, prior treatment failures, or patients looking to maximize healing potential, she may recommend adding bone marrow concentrate.
"Age and activity level do play a role," she notes. "An active athlete in their 40s with a substantial partial tear may benefit from a more robust biologic approach than a less active patient with mild tendinopathy." The decision ultimately comes down to the severity of the tissue damage, the patient's healing goals, and their overall activity demands.

Why MLS Laser Therapy Is Often Paired With the Injection
"Regenerative injections help provide the biologic building blocks for healing, while MLS laser therapy creates a more favorable healing environment," Dr. Etelzon explains. In practice, that often means performing the injection first, then following it with MLS laser treatments over the next several weeks to reduce inflammation, improve circulation, support cellular metabolism, and enhance tissue recovery.
"The goal isn't simply pain relief. It's to optimize the body's healing response," she says. The injection addresses the injured tissue directly, and the laser helps accelerate and support the recovery process, which is why the two are frequently used together in appropriate patients.
Cutting Through the Marketing Noise Around Stem Cells
"For many patients, the confusion comes from marketing," Dr. Etelzon says. She is direct with patients about what bone marrow concentrate actually is: "Bone marrow concentrate is not a magic cure, and it's not about growing a brand new shoulder. It's a concentration of the body's own repair cells, growth factors, and signaling molecules designed to support the natural healing process."
Her advice to patients is to "be skeptical and focus on the diagnosis, the quality of the procedure, and the available evidence, not the advertising." She frames the real goal of treatment as improving the biologic environment, reducing pain, enhancing function, and potentially delaying or avoiding more invasive treatment for the right candidate. Setting realistic expectations, she says, is one of the most important parts of the consultation.
What Recovery Actually Looks Like
"Recovery after regenerative treatment is generally much easier than recovery after surgery, but it's important for patients to understand that healing still takes time," Dr. Etelzon says. Most patients notice some soreness for several days after the procedure as the body's healing response gets underway. Over the first few weeks, the focus shifts to protecting the treatment area, restoring motion, and gradually increasing activity. There are no incisions, no implants, and typically no prolonged immobilization.
"Most patients can continue many of their normal daily activities within days, while meaningful improvements often develop gradually over the following weeks to months as the tissue heals," she explains. The biggest difference from surgery is the absence of a long rehabilitation period built around recovering from the procedure itself.
Getting Back to What Matters
For the women who come through Pain Doctors Medical's doors in Brooklyn, Clifton, Newark, and Perth Amboy, shoulder pain is rarely just about the shoulder. It's about the swim laps put off for months, the garden beds that have become too hard to kneel into, the grandchildren they want to lift without wincing. Regenerative medicine gives many of them a way back to those moments, with a recovery that fits into real life instead of replacing it for months.
If shoulder pain has started limiting what matters most, a consultation with Dr. Etelzon is a clear and simple next step.

What Is Regenerative Medicine and Is It Right for You?
Regenerative medicine is reshaping how physicians and patients think about healing. Rather than managing pain from the outside in, it works from the inside out, using the body's own biology to repair damaged tissue, restore function, and help people get back to the activities that make life worth living.
For patients who have spent years cycling through treatments that offer temporary relief but never quite solve the problem, regenerative medicine offers something different: a path toward actual healing.
Dr. Ilana Etelzon, MD, a double board-certified interventional pain specialist and Regenexx Core Provider at Pain Doctors Medical, has built her practice around this approach. Here, she explains what regenerative medicine actually does, how it works, and why the outcomes consistently go beyond what patients expect.
It Aims to Heal the Tissue, Not Just Quiet the Pain
Most patients arrive at Pain Doctors Medical having tried treatments that focused on managing their symptoms. That approach can be valuable. But it does not address what is actually wrong.
"Most treatments focus on managing symptoms," Dr. Etelzon says. "Regenerative medicine focuses on helping your body heal the underlying injury."
In practice, that means using the body's own healing cells and growth factors to support tissue repair, improve function, and potentially help patients avoid more invasive interventions. The goal is not temporary relief. It is helping the damaged area function better over the long term.
That distinction matters more than it might seem. Chronic pain is often a symptom of tissue dysfunction, not just a signal to be turned down. When the tissue itself heals, patients tend to experience more durable improvements, not just in pain levels but in what they can actually do.
What Is Actually Happening at the Tissue Level

One of the most common questions Dr. Etelzon gets is how regenerative treatments are different from a cortisone injection. The short answer: cortisone reduces inflammation and can provide meaningful relief, but it does not repair anything. Used repeatedly, it may actually have negative effects on tissue health over time.
Regenerative treatments work differently. They deliver concentrated growth factors and healing signals that help the body recruit repair cells, improve blood flow, and support the healing response within injured tissues. Tendons, ligaments, joints, and cartilage are given a biological environment in which they can recover.
"What many patients don't realize is that pain is often a symptom of tissue dysfunction," Dr. Etelzon explains. "While cortisone can quiet the pain signal, regenerative medicine aims to improve the health of the tissue itself, which may lead to more durable improvements in pain and function."
The Four Treatments at Pain Doctors Medical
At Pain Doctors Medical, Dr. Etelzon uses four core regenerative and supportive modalities: platelet-rich plasma (PRP) injections, bone marrow concentrate (often referred to as stem cell therapy), MLS laser therapy, and shockwave therapy. What sets her approach apart is that she rarely uses just one.
"In many cases, the best results come from combining treatments because healing is multifaceted," she says. "Just as you wouldn't build a house with only one tool, we often use a strategic combination of regenerative procedures and supportive therapies to create the best environment for healing."
Here is how each one works:
PRP injections use a concentrated preparation of the patient's own platelets, rich in growth factors. PRP is often well-suited for mild to moderate injuries and inflammation in tendons, joints, and soft tissue.
Bone marrow concentrate draws on the regenerative cells found in the patient's own bone marrow. It is typically reserved for more advanced degeneration or complex cases where a more potent biological signal is needed.
Shockwave therapy delivers acoustic energy to stimulate healing and improve blood flow, making it particularly useful in chronic tendon injuries that have been resistant to other treatments.
MLS laser therapy uses synchronized wavelengths of light to reduce pain and inflammation and support the recovery process, often used alongside other regenerative procedures.
The treatment plan for each patient starts from scratch. Dr. Etelzon considers the diagnosis, the severity of tissue damage, the patient's goals, and what they have already tried. No two plans look exactly the same.
Why the Regenexx Credential Matters
Regenerative medicine is a field where technique matters enormously. The quality of the biologic product, how it is processed, and the precision of where it is placed can all affect outcomes significantly.
Dr. Etelzon is a Regenexx Core Provider, which means she has completed advanced training in image-guided regenerative orthopedic procedures and follows strict clinical protocols. Regenexx procedures are performed using imaging guidance to accurately target the specific structures involved, rather than injecting a general area.
"It's not just about what is injected," Dr. Etelzon says. "It's about how, where, and why it's done. Those details can make a meaningful difference in the care patients receive."
Patients also benefit from protocols refined over many years and access to one of the largest regenerative medicine outcome databases in existence. That level of rigor is not universal in this space, and it is one reason patients travel to Pain Doctors Medical from across New Jersey and New York.
The Result That Surprises Patients Most
When patients come in, they are hoping their pain will improve. That is usually not the thing that surprises them.
"The biggest surprise is usually not the pain relief. It's getting their life back," Dr. Etelzon says. "I've had patients get back to golfing, hiking, playing tennis, traveling comfortably, exercising, getting down on the floor with their grandchildren, or simply walking without constantly thinking about their pain."
The activities patients describe are rarely extreme. They are things most people take for granted until they cannot do them anymore. A long walk. A flight without dread. A round of golf with friends. Weekend hikes. Time with grandchildren that does not end in pain.
The moment Dr. Etelzon finds most rewarding is when a patient says: "I stopped doing that years ago because I thought I'd never be able to again."
That is the metric regenerative medicine is measured by at Pain Doctors Medical. Not just pain scores. Restored function, restored confidence, and a return to the life the patient had before things started breaking down.
Is Regenerative Medicine the Right Next Step for You?
Regenerative medicine is not a fit for everyone, and Dr. Etelzon will tell you that directly. But for patients who have not found lasting relief through conventional treatments and are looking for an alternative to surgery or long-term medication, it is worth a real conversation.
Pain Doctors Medical sees patients at four locations: Clifton NJ, Newark NJ, Perth Amboy NJ, and Brooklyn NY. Consultations with Dr. Etelzon begin with a thorough evaluation of your history, imaging, and goals before any treatment is recommended.
If you have been quietly adjusting your life around pain for years, it may be time to find out whether there is another option.